
HMP Gartree
Report on an unannounced inspection of HMP Gartree by HM Chief Inspector of Prisons 3–13 August 2026

Introduction (Back to top)
Located near Market Harborough in Leicestershire, Gartree is a secure prison for long termers that fulfils a distinctive function. Its role is to contain risk and help prisoners address the factors that contributed to their offending, while maintaining hope and a sense purpose during long periods in custody. At the time of our inspection it held 631 men, all serving indeterminate sentences. Many had committed the most serious offences, and some faced many years at Gartree before there was any realistic chance they could progress.
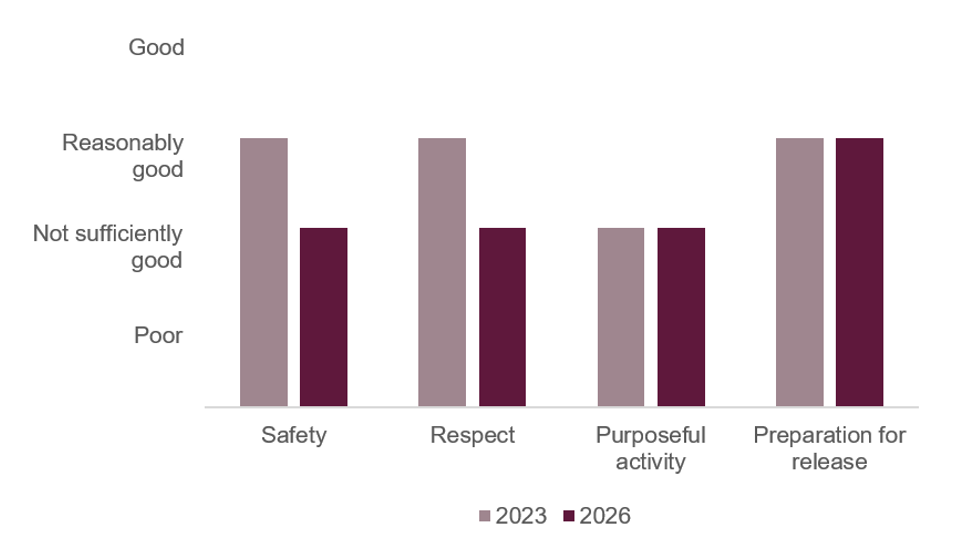
Against that backdrop, we found a prison that evidenced some notable strengths, but where outcomes for prisoners had deteriorated since our last inspection, most notably in Safety and Respect, which we now judged to be not sufficiently good. In Purposeful activity outcomes also remained not sufficiently good; only in Preparation of release did we see outcomes that were reasonably good.
There was much to commend in the leadership of the prison. The governor was well regarded by staff and prisoners alike and had successfully managed a significant change in population following the reopening of a wing in 2025. Despite staffing pressures, leaders had prioritised maintaining a full regime and most prisoners were able to spend a reasonable amount of time out of their cells. Specialist units, including the therapeutic communities, psychologically informed planned environment and incentivised substance-free living unit, provided impressive environments where positive relationships, personal responsibility and rehabilitation were actively promoted. The offender management unit was well led and supported prisoners’ progression usefully.
However, these strengths were outweighed by a number of serious concerns. Violence had risen substantially since our previous inspection, but behaviour management arrangements lacked rigour. Drugs remained readily available and continued to fuel debt, violence and instability. Three confirmed drug-related deaths since the last inspection illustrated the scale of the challenge. Self-harm had doubled and support for prisoners in crisis was too limited, with too few interventions available beyond formal case management processes.
Living conditions were also disappointing. The better standards established on the specialist units had not been replicated on the general accommodation wings; too many prisoners lived in accommodation that was dirty, poorly maintained and often lacked basic furnishings. There remained an extensive list of outstanding repairs and segregation conditions, in particular, continued to be wholly inadequate for the vulnerable and complex prisoners held there.
Healthcare outcomes were undermined by weak governance. We were particularly concerned by poor access to psychological therapies, significant delays in transferring severely mentally ill prisoners to hospital, and shortcomings in medicines management that meant some patients went without essential medication.
Education and work also required improvement. Leaders had not developed a curriculum sufficiently tailored to the needs and aspirations of this unique population, attendance was poor and too many prisoners were disengaged from purposeful activity.
Nevertheless, preparation for release remained reasonably good and there was evidence of committed staff working hard to support progression. The challenge for leaders now is to extend the standards and positive culture evident in the prison’s specialist units and replicate them across the wider establishment. We highlight a number of priorities and concerns in our report which we hope will assist that process.
Charlie Taylor, HM Chief Inspector of Prisons, September 2026
Outcomes for prisoners (Back to top)
We assess outcomes for prisoners against four healthy prison tests: safety, respect, purposeful activity, and preparation for release (see More about this report for more information about the tests). We also include a commentary on leadership in the prison (see Section 1).
At this inspection of HMP Gartree, we found that outcomes for prisoners were:
- not sufficiently good for safety
- not sufficiently good for respect
- not sufficiently good for purposeful activity
- reasonably good for preparation for release.
We last inspected HMP Gartree in 2023. Figure 1 shows how outcomes for prisoners have changed since the last inspection.
Figure 1: HMP Gartree healthy prison outcomes 2023 and 2026
What needs to improve (Back to top)
During this inspection we identified 14 key concerns, of which six should be treated as priorities. Priority concerns are those that are most important to improving outcomes for prisoners. They require immediate attention by leaders and managers.
| Priority concerns | |
| 1. | Violence was increasing, and behaviour management processes were insufficient. |
| 2. | The ingress of drugs and illicit items was impacting the safety and stability of the prison. |
| 3. | The rate of self-harm had doubled since our last inspection. There were too few interventions available to support prisoners in crisis. |
| 4. | Many areas of the prison were unclean and poorly maintained, and not all cells were adequately furnished. |
| 5. | Patients had limited access to psychological therapies, which meant longstanding trauma and distress remained unaddressed. |
| 6. | Leaders had not developed a cohesive education, skills and work (ESW) curriculum that aligned to prisoners’ interests, aspirations and potential career paths in prison and beyond. |
| Key concerns | |
| 7. | The segregation unit was in poor condition. There was no holding room, exercise yards were cage-like, and the single shower had mould. |
| 8. | The supply of medicines was unreliable, which meant that prisoners sometimes ran out of medication. Oversight of medicines management was poor, and medicine storage did not meet national standards. |
| 9. | Severely mentally ill individuals, who required treatment in hospital under the Mental Health Act, continued to experience prolonged delays. |
| 10. | The reading strategy was not fully implemented, which limited prisoners’ access to the curriculum. |
| 11. | Prisoners did not have access to a suitable personal development curriculum. Activities designed to develop prisoners’ interests beyond the education curriculum were limited. |
| 12. | Prisoners’ attendance and punctuality to ESW, particularly in work activities that prepared prisoners for further work and study, was low. The sequencing of initial assessments was poor and delayed allocation to activities. |
| 13. | The quality of education, skills and work across the prison was not good enough. Several industry staff had not received sufficient training to effectively operate their workshops. |
| 14. | There were delays in reviewing phone calls for prisoners subject to offence-related monitoring, which undermined work to protect the public. |
Notable positive practice (Back to top)
We define notable positive practice as evidence of our expectations being met to deliver particularly good outcomes for prisoners, and/or particularly original or creative approaches to problem solving. Inspectors found an example of notable positive practice during this inspection, which other prisons may be able to learn from or replicate.
| 1. | The incentivised substance-free living (ISFL; see Glossary) unit provided a community ethos that helped support patients living substance free and included a group of peer workers, known as ‘culture carriers’, who promoted positive behaviour as a key component of the unit. (See Security and Support and treatment for prisoners with addictions and those who misuse substances). |
Unless otherwise specified, these examples are not formally evaluated, are a snapshot in time and may not be suitable for other establishments. They show some of the ways our expectations might be met, but are by no means the only way.
Section 1: Leadership (Back to top)
Leaders provide the direction, encouragement and resources to enable good outcomes for prisoners.
Leaders had managed well an influx of new prisoners in the summer of 2025 following the reopening of a wing but were still adjusting to the needs and security risks of a more challenging indeterminately sentenced population.
The governor, who was well regarded by both staff and prisoners, provided visible leadership and had clearly communicated her priorities. In our survey, 83% of staff who responded said that leaders’ priorities were communicated to them very/quite clearly, and 79% agreed with these priorities.
Despite only 75% of the prison’s quota of officers being available for duties, the governor had prioritised operating a full regime, and most prisoners had a good amount of time unlocked. However, the education, skills and work strategy did not align well with the needs of long-term prisoners, and attendance had recently declined.
Leaders had plans to strengthen an under-resourced safety team in response to increasing rates of violence and self-harm. Installation of window grilles to tackle the increased ingress of drugs via drones was imminent.
Responding to the long-term high security estate’s plan to reduce violence, leaders had minimised the impact on the wider population by only restricting the regime for the most violent offenders. However, the arrangements in place for such prisoners were equivalent to segregation, and support for these individuals was inadequate.
The head of psychology led a service that was well integrated with the operations of the prison, and there had been a temporary shift of psychology resource from programme delivery to better support the safety of both staff and prisoners. There were plans to extend the current regular supervision for officers working with segregated prisoners and in the specialist units, to include reflective practice for staff on other units. Weekly business meetings were also held on the residential units and psychologically informed one-page plans for the management of complex prisoners were shared with staff.
Leaders had not sufficiently prioritised or improved standards of cleanliness and decency on the older wings, which remained dilapidated, and too many repairs by the facilities management provider, Amey, were outstanding.
Although partnership working was reasonably effective, governance and oversight by health care leaders of medicines management and mental health was weak.
The offender management unit (OMU; see Glossary) was well led by visible, supportive and experienced managers whose open-door approach and regular supervision contributed to a culture of high standards.
While the specialist units, including the psychologically informed planned environment (PIPE; see Glossary), therapeutic communities (TCs; see Glossary) and an ISFL unit, provided good rehabilitative environments, their community ethos had not spread or been instilled across the other residential units. This limited opportunities for the majority of prisoners to develop a sense of purpose and hope.
Section 2: Safety (Back to top)
Prisoners, particularly the most vulnerable, are held safely.
Early days in custody
Expected outcomes: Prisoners transferring to and from the prison are safe and treated decently. On arrival prisoners are safe and treated with respect. Risks are identified and addressed at reception. Prisoners are supported on their first night. Induction is comprehensive.
The prison received few new arrivals each month, though there had been an influx in the summer of 2025 following the re-opening of a residential unit.
The reception was cramped and barely fit for purpose. Holding rooms had televisions and some information for prisoners to read, but there was little space in which to process prisoners and their property. Peer workers were not typically present in reception to speak to prisoners.

Staff deployed to reception were friendly and worked hard to process prisoners quickly despite the challenging environment. Prisoners had an interview with an officer in private to ascertain their risks before being taken to the induction unit. In our survey, 82% of prisoners said that they felt safe on their first night.


| HMIP prisoner survey | Yes | Compared with similar prisons |
| Before you were locked up on your first night here, were you offered? | ||
| Nicotine replacement (including vapes) | 57% | Lower |
| Something to eat | 23% | Lower |
| Support from another prisoner (e.g. Insider or prisoner rep) | 63% | Lower |
However, prisoners reported more negatively in our survey than at similar prisons about receiving items and support on their first night. Late arrivals at the prison contributed to this, limiting the time available to staff to make arrangements.
Prisoners could not access any canteen items until their first order, which could take almost two weeks to arrive and increased the risk of prisoners falling into debt.
The induction unit was tired, and first night cells we viewed were often in poor condition. Some prisoners we spoke to, who had recently arrived, did not have furniture such as tables and chairs (see Living conditions).



Prisoners received an induction over their first two weeks in the prison, but this did not include any formal arrangements for peer support. Different departments of the prison visited prisoners but local records indicated that these visits were not always timely.
Promoting positive behaviour
Expected outcomes: Prisoners live in a safe, well ordered and motivational environment where their positive behaviour is promoted and rewarded. Unacceptable conduct is dealt with in an objective, fair, proportionate and consistent manner.
Encouraging positive behaviour
| Data provided by the prison | |
| Rate of violent incidents per 1,000 prisoners in the 12 months to June 2026 | 296 |
The overall rate of violence had increased by 53% since the previous inspection. Assaults on staff had risen by 49%, while prisoner-on-prisoner assaults had increased by 63%. However, the rate of serious assaults had fallen by 20%.
In our survey, around half of prisoners reported having felt unsafe at some point during their time at the prison, and approximately a quarter said they currently felt unsafe, but this was similar to findings at comparator prisons.
Leaders told us that the illicit prison economy was a key driver of violence, with debt and associated bullying contributing to many assaults.
Leaders had introduced a ‘violence reduction landing’ on G wing to help address the rise in violence. Several men, who had perpetrated violent incidents, were separated there away from other prisoners. However, at the time of our visit, the regime was comparable to segregation, and there was little to support or challenge individuals. There were credible plans to develop a more therapeutic approach, but prisoners described high levels of frustration at their current situation.
Challenge, support and intervention plans (CSIPs; see Glossary) were of variable quality. Improvements were needed in both the quality of investigations and the development of meaningful plans.
There were around 11 prisoners isolating for their own safety who were managed through the CSIP process. Although they mostly received an adequate regime, more needed to be done to support individuals and facilitate their reintegration, particularly as many had lengthy periods left to serve.
An additional ‘enhanced two’ level had been added to the incentives scheme to provide greater impetus to behave well, However, prisoners told us that this was still not enough. Our review of case notes found that during the previous 28 days, 80% of case entries recorded negative behaviour rather than recognising or encouraging positive conduct.
There had been 3,269 adjudications in the previous 12 months, compared with approximately 2,000 at the last inspection. The most prevalent charges were for assaults and illicit items, reflecting the higher levels of violence and drug use across the prison.
Too many adjudications remained outstanding. More than 600 cases had not been dealt with, reducing the effectiveness and credibility of the process and undermining deterrence and accountability with respect to behaviour management.
Use of force
| Data provided by the prison | |
| Annual number of recorded use of force incidents in the 12 months to June 2026 | 700 |
The rate of use of force had increased by 160% since the previous inspection. However, just under a third of incidents concerned the precautionary application of handcuffs used when moving prisoners during a lockdown search in May 2026.
PAVA incapacitant spray (see Glossary) had been drawn 36 times during the previous 12 months and deployed on 24 occasions. At the last inspection, it had been drawn on only five occasions. These incidents were subject to appropriate scrutiny, and our review of body-worn camera footage did not identify any inappropriate uses.
Governance arrangements for the use of force had recently improved. All incidents were triaged by a multidisciplinary team to ensure appropriate oversight.
The use-of-force coordinator had delivered incident management training to new officers to improve their confidence and capability in managing challenging situations.
There had been one use of special accommodation during the previous 12 months, which was justified and appropriately authorised.
Segregation
In keeping with findings at the last inspection, the segregation unit remained almost full, with several complex prisoners, some held for prolonged periods. At the time of our visit, for example, six men were being appropriately supported through assessment, care in custody and teamwork (ACCT; see Glossary) case management because they were at risk of suicide and self-harm.
In response to the rising violence, some prisoners were also segregated on the ‘violence reduction landing’ on G wing, as there was a lack of space in the segregation unit (see Encouraging positive behaviour). Although co-location on this wing enabled closer supervision and oversight, the regime remained poor and support was inadequate.
Living conditions on the segregation unit remained poor. The single shower contained mould, and the cage-like exercise yards were bleak. The unit was not fit for purpose and, as at the previous inspection, required refurbishment.


The regime remained limited, consisting primarily of access to a shower and daily exercise. However, some physical exercise sessions and in-cell activity workbooks had recently been introduced.
During our visit, around 30 prisoners from elsewhere in the prison used the three segregation unit exercise yards, which placed additional pressure on the regime. Prisoners located on the ‘violence reduction landing’ and those who were self-isolating or unable to exercise with others were escorted to the unit for time in the open air.
There was good input from psychologists to support segregated prisoners. Supervision also provided for staff helped the effective management of challenging individuals; for example, by advising how to best communicate with these prisoners. We saw respectful interactions from staff towards prisoners on the unit.
Security
Expected outcomes: Security and good order are maintained through an attention to physical and procedural matters, including effective security intelligence and positive staff-prisoner relationships. Prisoners are safe from exposure to substance misuse and effective drug supply reduction measures are in place.
| Data provided by the prison | |
| Positive random drug test rate (MDT) in the 12 months to June 2026 | 16% |
The illicit economy represented the most substantial threat to the safety and security of the prison.
Since the previous inspection, there had been three confirmed deaths involving the use of illicit substances, as well as two further non-natural deaths.
In our survey, 52% of prisoners reported that it was easy or very easy to obtain illicit drugs, which was similar to the comparator. Leaders acknowledged that drugs were readily available within the prison, and during the inspection we detected the smell of illicit substances in use.
Leaders told us that drones were the main route of ingress for illicit items, and good muti-agency work with the police was helping to address this. The security team were aware of other routes of ingress and managed these risks, for example, by operating enhanced gate security 24 hours a day.
The governor had appointed a dedicated drug strategy lead during the previous year, and work to develop recovery support within the prison had improved.
The impressive ISFL unit provided support to a small number of prisoners seeking to remain free from illicit substances (see Support and treatment for prisoners with addictions and those who misuse substances).

There were frequent difficulties in accurately accounting for prisoners’ whereabouts, which led to disruption to the regime. Leaders were addressing this through the introduction of new roll check reconciliation procedures, but the issue continued to affect movement around the site (see Time out of cell).
Leaders had a good understanding of the risks associated with extremism and corruption, and these were managed effectively. There was constructive engagement with external partners, including the police and counter-terrorism teams.
Some prisoners had reported concerns about the fairness of searching procedures. The deputy governor was addressing this by actively monitoring this area to ensure that the dedicated search team conducted searches in a procedurally just and respectful manner.
Safeguarding
Expected outcomes: The prison provides a safe environment which reduces the risk of self-harm and suicide. Prisoners at risk of self-harm or suicide are identified and given appropriate care and support. All vulnerable adults are identified, protected from harm and neglect and receive effective care and support.
Suicide and self-harm prevention
The rate of self-harm had doubled since our last inspection but remained below the average for category B training prisons. The prison held some complex individuals, some of whom had been managed through segregation for lengthy periods (see Segregation). In the last year, around half of incidents related to just six men.
There had been two self-inflicted deaths since the previous inspection. Leaders had only recently introduced checks on Prisons and Probation Ombudsman (PPO; see Glossary) recommendations to ensure that they were being addressed.
Support for prisoners at risk of self-harm was underdeveloped. There were few interventions available to support prisoners or prevent them from falling into crisis, outside of ACCT case management. Some men we spoke to spent long periods locked up as they lacked employment and had little to occupy them. We found several instances where staff had missed opportunities to prevent individuals from deteriorating.
The safety team, despite some investment by leaders, was small, which limited the support it could offer staff and prisoners. Some complex individuals nevertheless benefited from effective multidisciplinary support.
| HMIP prisoner survey | Yes | Compared with our last inspection |
| For those who have been on an ACCT: Did you feel cared for by staff? | 26% | Lower |
In our survey, not enough prisoners subject to ACCT case management said they felt cared for by staff, which was a big drop from around two-thirds at our last inspection. Plans were basic, or in some cases missing, and actions identified to support prisoners were frequently generic or did not fully address prisoners’ issues.
Investigations into serious incidents of self-harm were taking place, but these did not sufficiently explore the reasons for incidents taking place, nor identify learning to help prevent similar incidents in the future.
The prison had increased the number of trained Listeners (see Glossary) to 15, an improvement from the last inspection, and they were made available to prisoners on request. A suite for Listener calls was available, but it was austere.

Protection of adults at risk
Leaders were prioritising improvements to safeguarding processes; the monthly SHARE (support, help, assess, refer and engage) meeting between prison and health care staff was a helpful forum for discussing prisoners with potential safeguarding issues.
Section 3: Respect (Back to top)
Prisoners are treated with respect for their human dignity.
Staff-prisoner relationships
Expected outcomes: Prisoners are treated with respect by staff throughout their time in custody and are encouraged to take responsibility for their own actions and decisions.
| HMIP prisoner survey | Yes | Compared with our last visit |
| Do most staff here treat you with respect? | 71% | Lower |
| Are there any staff here you could turn to if you had a problem? | 67% | Lower |
| In the last week, has any member of staff talked to you about how you are getting on? | 37% | Lower |
Prisoners were more negative in our survey about relationships with staff than at the time of our last inspection but were more positive than at similar prisons.
This was reflected on residential units. While we observed generally respectful interactions between staff and prisoners, and officers were visible on landings, exchanges were often brief and transactional. Prisoners expressed frustration about difficulties getting staff to take time to listen to them or address their issues.
The design of some of the older wings made them challenging to supervise day-to-day. On some landings we saw blocked observation panels, although low-level poor behaviour was uncommon.
Leaders were prioritising some groups for regular key work (see Glossary), but in cases we reviewed, sessions were too infrequent and not sufficiently focused on progression. Despite this, we saw some examples of good key work taking place on specialist units, which were better resourced (See Specialist units).
Peer support was used effectively in some areas, such as the ISFL and in education, but this was not consistent across the prison (see Early days in custody).
Daily life
Expected outcomes: Prisoners live in a clean and decent environment and are aware of the rules and routines of the prison. They are provided with essential basic services, are consulted regularly and can apply for additional services and assistance. The complaints and redress processes are efficient and fair.
Living conditions
| HMIP prisoner survey | Yes | Compared with similar prisons |
| Do you normally have enough clean clothing that fits you? | 50% | Lower |
Although prisoners lived in single-cell accommodation, standards varied across the prison. Cells on the older wings (A, B, C and D) were cramped; often lacked furniture, including tables, cupboards and chairs; and toilets had no privacy screen. In contrast, cells on the newer and smaller specialist units were appropriately equipped.
Leaders had not done enough to ensure acceptable standards of cleanliness across the prison. Conditions on the older wings remained poor, with many areas affected by ingrained dirt and damaged flooring which required replacement. Communal areas on the newer and smaller specialist units, by way of contrast, were generally well maintained and provided a more supportive living environment.


Despite some refurbishment, shower areas on the older wings were unclean. However, prisoners reported more positively than those in comparable prisons about their ability to access showers. Although 70% of prisoners reported in our survey that they could get cleaning materials every week if they wanted them, both staff and prisoners told us during our visit that there were frequent shortages, including of mops.


Litter and food were frequently thrown from cell windows on the older units. Even with regular cleaning by prisoner work parties, the areas surrounding some accommodation blocks had litter. On the small specialist units, prisoners had developed gardens that supported well-being and fostered a community ethos.

Staff were proactive in identifying and reporting maintenance issues. However, there was a substantial backlog of more than 600 outstanding repairs by the facilities manager provider Amey.
Many prisoners told us that they had limited clothing, including prison clothing. Only prisoners on the ‘enhanced two’ level of the incentives scheme could have an annual clothing parcel delivered. Other prisoners said they had insufficient funds to buy clothes from catalogues. Staff shortages also contributed to frequent delays in prisoners receiving their property, which was a common source of frustration.
In our survey, 36% said their cell call bell was answered within five minutes, which was better than at similar prisons.
Residential services
In our survey, more prisoners than at similar prisons said that they usually got enough to eat at mealtimes. Meals we observed were of reasonable quality and size.

The kitchen was tired and showing signs of age, but it was clean, well-ordered, and provided a good variety of meals. Kitchen staff were working around some equipment failures during our visit and were also reliant on temporary freezers.
Prisoners working in the kitchen could only gain a level 2 food safety qualification but were assigned a variety of roles that supported the development of different skills, such as baking and planning portions for the week.
Consultation arrangements were reasonable; the catering manager attended the prison council, and food representatives on wings attended forums to provide feedback, although these were not taking place consistently.
Self-catering facilities on wings were often cramped and limited to a few appliances such as toasters, microwaves and sandwich grills. Those that were available were often dirty or in poor condition.


Canteen and catalogue ordering processes were functioning effectively. Refunds for missing items were processed promptly.
Prisoner consultation, applications and redress
| Data provided by the prison | |
| Number of submitted complaints per 1,000 prisoners (July 2025–June 2026) | 6,550 |
Well-attended prison council meetings were chaired by a prisoner and attended by the governor. Progress was tracked and meeting minutes were published in the monthly prison magazine, but some actions took too long to implement. Monthly wing representative forums were held but only intermittently, reducing their effectiveness.
Prisoners continued to submit applications using paper forms, and many told us that responses were either delayed or not received at all. Leaders acknowledged weaknesses in the oversight of the applications process, particularly in relation to the timeliness and quality of responses, and they were piloting new arrangements to improve outcomes and build prisoner confidence in the system.
Complaints had increased by 34% since the last inspection. Complaint handling was generally effective, with responses usually timely, fair, and courteous. Leaders made effective use of complaint data to identify recurring themes but had been slow to address the underlying causes of the high volume of property complaints.
Access to face-to-face legal visits had improved. Additional appointments were now available, and meetings took place in private booths. However, official prison video conferencing (see Glossary), a previously popular facility, had been unavailable for five months while arrangements were made to relocate the service.
Fair treatment and inclusion
Expected outcomes: There is a clear approach to promoting equality of opportunity, eliminating unlawful discrimination and fostering good relationships. The distinct needs of prisoners with particular protected characteristics (see Glossary) or those who may be at risk of discrimination or unequal treatment, are recognised and addressed. Prisoners are able to practise their religion. The chaplaincy plays a full part in prison life and contributes to prisoners’ overall care, support and rehabilitation.
| Data provided by the prison | |
| Proportion of prisoners who were from ethnic groups other than white at the time of the inspection | 40% |
| Proportion of prisoners who were foreign nationals at the time of the inspection | 13% |
| Proportion of prisoners who were neurodivergent (including self-reporting) at the time of inspection | 43% |
Support for fair treatment was reasonable, and senior managers had been allocated responsibility for leading on individual protected characteristics. Regular opportunities for consultation, however, were limited. For example, 40% of the population were from minority ethnic backgrounds, yet only two prisoner focus groups had taken place in the previous 12 months.
Equality meetings, data and discrimination complaints identified several recurring themes, including staff not respecting religious materials, concerns about food provision and the disproportionate searching of minority ethnic prisoners. However, oversight lacked rigour and little had been done to correct or explain these disparities.
During the inspection, some prisoners from minority ethnic backgrounds described experiencing disrespectful treatment from a small number of officers, particularly during searches. These findings were reflected in our survey, where prisoners from minority ethnic groups reported more negatively on several aspects of prison life, including consultation, support from managers and experiences of staff bullying.
Support for neurodivergent prisoners on the therapeutic community units was good; provision for those living on the main wings was too limited. The absence of a neurodiversity support manager for over a year had limited the identification of need and the support available, and again, there had been no consultation with this group of prisoners.
The prison had provided a dedicated over-50s wing, but retired prisoners were not routinely unlocked during the working day (see Time out of cell). Some older and disabled prisoners had to use free-standing shower chairs in their cells because suitable cell seating had not been provided. Peer support ‘buddies’ helped older prisoners and those with physical disabilities to manage daily activities (see Social care), but a lack of suitable seating on the exercise yards restricted access to outside areas.

The foreign national casework coordinator provided useful support but there was insufficient oversight of prisoners with limited or no understanding of English, and professional interpreting services were not used consistently. In our survey, only 5% of foreign national prisoners said it was easy to speak to a manager or governor, compared with 39% of British prisoners.
Support for young adult prisoners was good. Regular consultation forums had led to positive changes, including improvements to visits clothing arrangements and family days. Two dedicated prison offender managers provided ongoing support to young adults, including transitional support for those newly arriving at the prison.
| Data provided by the prison | |
| Number of submitted DIRF’s per 1,000 prisoners (July 2025–June 2026) | 483 |
The number of discrimination incident reporting forms (DIRFs; see Glossary) submitted had increased since the last inspection. Those we reviewed were generally investigated thoroughly and responded to appropriately. Recent independent scrutiny by the Zahid Mubarek Trust (see Glossary) had identified areas for further improvement and some staff training was planned.
Faith and religion
The chaplaincy team was well embedded across the prison and, despite vacancies, continued to provide a good level of faith support. Recently bereaved prisoners were supported by a team that coordinated prisoner donations and offered practical and emotional assistance, including additional telephone credit, wreaths, and a book of condolence.

Health, well-being and social care
Expected outcomes: Patients are cared for by services that assess and meet their health, social care and substance use needs and promote continuity of care on release. The standard of provision is similar to that which patients could expect to receive elsewhere in the community.
The inspection of health services was jointly undertaken by the Care Quality Commission (CQC) and HM Inspectorate of Prisons under a memorandum of understanding agreement between the agencies. The CQC found breaches of regulations and issued a request for an action plan following the inspection (see Appendix II).
Strategy, clinical governance and partnerships
| HMIP prisoner survey | Yes | Compared with similar prisons |
| Do you think the overall quality of the health services here is very/quite good? | 25% | Lower |
Practice Plus Group provided healthcare under a prime provider model, with Midlands Partnership University NHS Foundation Trust subcontracted to deliver psychosocial substance misuse services. Access to healthcare was variable, and patient feedback was more negative than at similar prisons.
Governance arrangements were in place but were not, for example, effective in ensuring patients received timely care. Available data was not used well enough to monitor performance or identify emerging concerns. Significant risks, particularly in relation to medicines management and mental health services, had not been properly identified or addressed.
The risk register did not adequately reflect the scale and impact of significant weaknesses in service provision, governance and staffing. Important risks were either absent or understated, including substantial gaps in access to psychological therapies needed by the population and weaknesses in medicines management. As a result, senior leaders did not have sufficient oversight of key risks or assurance that effective mitigating action was being taken.
Staff interactions with patients were professional and respectful. Staff felt well supported and had good opportunities for development through experience and formal learning. Clinical supervision was readily available, and most staff were up to date with mandatory training.
While partnership with the prison was reasonably effective, there were ongoing challenges with clinics not starting promptly due to regime slippages (see Time out of cell).
The health care facility was spacious and clean but there was no option for wing-based clinical work due to lack of suitable space. This posed challenges for some elderly and disabled patients who had to attend the health care centre to access clinical care.
Clinical audit was used effectively across some areas to monitor improvements and ensure safe working practice could be sustained. Management of complaints was variable, with some acknowledgements and responses outside of expected timescales. There was evidence of a good reporting culture, which supported learning from incidents and patient feedback. However, duty of candour needed to be more consistently applied and shared with patients.
Record keeping met the required standard with appropriate assessments for scheduled and unscheduled care, clear narratives and good quality personalised care plans, many of which had been co-produced.
Emergency medicines and equipment was located around the prison and subject to regular weekly checks. Staff had not received specialist training in some items within the emergency bags, and these were removed during the inspection.
Promoting health and well-being
There was no whole prison health promotion strategy, although there was evidence of joint working to plan some events from the annual calendar.
Patient forums were facilitated by the patient experience lead, who supported a group of health care representatives, however, they had not received any training for their role.
Patients had access to NHS health checks, national screening programmes, vaccinations and bloodborne virus screening. There was a reasonably good level of uptake, especially for the bowel screening programme.
Sexual health clinics were provided monthly and as needed for any urgent requirements. Condoms were available on request.
Disease outbreak plans were in place with good links to strategic public health advisers.
Primary care and inpatient services
The primary care team was small and well organised, ensuring all activity was covered daily. The team worked in close partnership with mental health and pharmacy teams to support patients.
New arrivals were seen for a comprehensive health screen and were discussed as part of the early days in custody pathway. Needs were identified and appropriate consent gained to make the required referrals.
Applications to see health care were collected by night staff and triaged daily. Nurse-led clinics were available daily, and access to the GP was good with the longest wait two weeks and three days. Daily embargoed appointments were available for patients with urgent needs.
Long term conditions were well managed, and additional training was scheduled to upskill all staff in this area. Annual reviews were up to date with good oversight and monitoring.
Waiting times for the podiatrist and optician were too long at 15 weeks. Secondary care appointments were well managed, but we were concerned that emergency transfers to hospital resulted in routine appointments being cancelled, disrupting the delivery of planned care.
No one was currently in receipt of palliative care but there had been good person-centred care for a patient in the last 12 months who received end-of-life care on the Acorn unit. Complex patients were managed effectively through the multi-professional complex case conference process.
Social care
The recently signed memorandum of understanding between the local authority (LA), Practice Plus Group and the prison underpinned effective partnership working to meet patients’ social care needs. We found no evidence of unmet need.
There was close collaboration between the prison and health care department with regular monitoring of patients with health vulnerabilities. Referrals to the LA for assessment were completed, and we saw evidence of appropriate in-cell adaptions to support individuals.
Patients were screened on arrival and referrals made to the LA, if necessary, for further assessment of need. At the time of the inspection, five prisoners were in receipt of a social care package (see Glossary). It was notable that social care staff used a ‘strengths-based’ approach which focused on supporting patients to maintain their abilities as far as possible and this was reflected in the good quality record keeping which mirrored this approach.
A ‘buddy’ system of peer support had been established on the wings which had included a range of appropriate training. The ‘buddies’ were well supervised and were appreciated by those they supported.
Mental health
Mental health services were delivered seven days a week by a small team of mental health nurses. Governance and oversight, particularly of psychological therapies, was not robust.
New arrivals were screened to identify any mental health need, and there was enhanced monitoring and support for those arriving with an increased risk of suicide.
The team received around 45 referrals a month and saw all non-urgent cases within five days and urgent cases within 48 hours.
Access to psychological therapies was poor. Ongoing vacancies for a psychologist, assistant psychologist and neurodiversity practitioner had resulted in insufficient capacity to meet patients’ needs. Some patients had waited more than 18 months for an assessment, and those who had been assessed had little prospect of receiving the psychological interventions they required because only one practitioner was available. There was clear evidence of significant unmet need. Given the longstanding and complex trauma experienced by many patients, the lack of timely psychological support was unacceptable and did not meet the requirements set out in the service’s own operating procedure.
The weekly multidisciplinary referral meetings provided some oversight and ensured that patients received the most appropriate care from the staff available. Patients experiencing mental health distress or crisis had access to the daily duty worker who also attended all ACCT reviews. Mental health staff visited patients in segregation daily. Arrangements for patients to see a psychiatrist were responsive.
Annual physical health monitoring was offered, in line with expectations and patients who did not attend were followed up.
All prison officers we spoke to had received some basic information about the mental health team and knew how to make referrals if they had concerns.
In the previous 12 months, five patients had required transfer to specialist mental health services under the Mental Health Act. Despite regular meetings with NHS commissioners to escalate severe delays, we saw little progress on waiting times, with the waits for the last two patients being 329 and 229 days.
Support and treatment for prisoners with addictions and those who misuse substances
There was good joint working between the prison and psychosocial substance misuse provider. A weekly meeting to discuss holistic management of patients under the influence or with a positive MDT result was a good initiative.
Around 30 patients were in receipt of clinical substance misuse treatment, and their care was well managed. Joint reviews were undertaken between clinical staff and recovery workers, which was good.
The psychosocial team assessed all new referrals promptly and offered excellent support to around 140 patients. There was a wide variety of interventions including one-to-one support, harm reduction, brief intervention group work for psychoactive substance use, and the structured group work programme: Inspire, Believe and Thrive.
Recovery planning for patients was person centred, and the team received positive feedback from their patients. Peer mentors and recovery champions provided invaluable support to patients across the prison.
The ISFL wing provided a bespoke environment with excellent facilities and a community ethos to support patients living substance free. A group of patients known as ‘culture carriers’ promoted positive behaviour on the wing, and staff showed passion and enthusiasm in supporting their patients on the unit (see Security).
Medicines optimisation and pharmacy services
Medicines were supplied by an external pharmacy, but arrangements did not ensure that they were consistently available when needed. Some monitoring had been introduced, but delays in supply were not reported as incidents and there had been no investigation of the impact of missed doses on patient outcomes. This was a significant gap in medicines governance and insufficient assurance that risks to patients were being identified and addressed.
Patients who held their own medicines (75% of the population) told us that the supply of repeat prescriptions was unreliable and that they sometimes ran out of medication. Complaints about medicines supply were increasing.
| HMIP prisoner survey | Yes | Compared with similar prisons |
| Since arriving in this prison, have you experienced any delays accessing your medication? | 83% | Higher |
Governance of medicines was poor: there was no pharmacist on site, medicines management meetings had not taken place for more than three months, and some written procedures were out of date. Medicines were not always stored securely: cabinets in the pharmacy did not meet required standards and could not be locked. The medicines fridge was overstocked, creating a substantial risk of stock loss if the required temperature could not be maintained and potentially affecting continuity of treatment.
Patients did not have access to pharmacist-led clinics, which was a gap.
The transfer of medicines across the prison had improved and was undertaken in appropriate lockable containers.
Medicines administration took place three times per day, and we observed respectful interactions between patients and staff. There were procedures for patients who missed medicines, and there was good follow up.
Hatches were suitably managed by prison officers, but they provided limited confidentiality. Nursing staff took medicines to the segregation unit and to people on the residential wings as necessary.
Staff reviewed in-possession risk assessments as required.
Although infrequent, medicines were provided for patients being transferred or released.
Dental services and oral health
Time for Teeth provided a range of dental treatments but staffing shortages had led to a backlog of around 100 patients who had waited up to four months for a new appointment. An additional 90 patients were awaiting follow-up treatment. Additional sessions had been commissioned to address the backlog and reduce waiting times.
The dental nurse triaged applications weekly when on site but locum cover had resulted in delays of up to two weeks for applications to be reviewed. This created a risk that urgent needs may not be identified in a timely manner. Urgent care was prioritised during clinics and pain relief and antibiotics were available if needed.
The dental suite was well equipped with a clear decontamination flow, but some tool cupboards did not lock and this needed to be addressed. Equipment was suitably maintained and serviced. Governance systems were robust.
Section 4: Purposeful activity (Back to top)
Prisoners are able and expected to engage in activity that is likely to benefit them.
Time out of cell
Expected outcomes: All prisoners have sufficient time out of cell (see Glossary) and are encouraged to engage in recreational and social activities which support their well-being and promote effective rehabilitation.
Around 62% of prisoners, who were in full-time employment, had a good amount of time out of their cell and could be unlocked for more than nine hours a day. Those who were unemployed or not required to work, including retired prisoners, were unlocked for only around three and a half hours.
At weekends, prisoners were scheduled to spend just over six hours out of their cell a day, but frequent curtailments caused by staff shortages meant that they were often unlocked for substantially less time.
In our roll check, we found a third of prisoners locked in their cells during the core working day; considerably higher than at the last inspection (5%). Regime slippage, caused by inaccurate roll checks, was a persistent problem and caused delay and cancellation to many activities and appointments (see Security). Only 53% of prisoners were engaged in education, training, or work; similar to the previous inspection (50%).
Access to outdoor exercise was limited to 45 minutes a day because there were not enough exercise yards. Some prisoners who were isolating for their own safety routinely went without exercise.
| HMIP prisoner survey | Yes | Compared with similar prisons |
| In a normal week, can you go to the gym or play sports three times or more? | 56% | Higher |
PE facilities were good, offering a broad range of activities, including bespoke sessions for prisoners on the TCs, ISFL and over-50s units. Prisoners in full-time activity could access up to six gym sessions a week.

The library was well stocked and a welcoming environment. Prisoners could apply to attend twice a week and take part in activities including language lessons and book, chess, and origami clubs. Shannon Trust (see Glossary) mentors provided reading support, and prisoners could use one of nine computers to develop basic digital skills.
In our survey, 56% of participants said they were able to visit the library once a week or more compared to 38% at similar prisons, but the library was no longer open at weekends.

Education, skills and work activities
Expected outcomes: All prisoners are expected and enabled to engage in education, skills or work activities that increase their employability on release. There are sufficient, suitable education, skills and work places to meet the needs of the population and provision is of a good standard.

Ofsted inspects the provision of education, skills and work in custodial establishments in England. The following summary has been provided by Ofsted inspectors who attended this inspection. Their full report is published under ‘Survey materials and Ofsted full report‘.
Ofsted made the following assessments about the education, skills and work provision:
- Overall effectiveness: Requires improvement
- Quality of education: Requires improvement
- Behaviour and attitudes: Requires improvement
- Personal development: Requires improvement
- Leadership and management: Requires improvement
Leaders had not fully resolved the recommendations from the previous inspection. Leaders did not have a clear, purposeful intent for their offer at HMP Gartree. The quality of education, skills and work (ESW) was still not good enough and leaders had not properly reviewed the curriculum to ensure it met prisoners’ needs.
Leaders had broadened their curriculum offer to provide more purposeful activity across ESW. There were generally sufficient spaces for prisoners to access ESW opportunities. Leaders had recently opened a ‘handyman’ workshop and increased spaces in a few industries workshops.
Mentors supported their peers across ESW activities well. They were trained, deployed and used very effectively in their various settings. This was a stand-out, positive feature in ESW.
The allocations process was unnecessarily complicated. It did not work efficiently for prisoners who wanted to change jobs or access other learning and development opportunities. Prisoners were not allocated to ESW based on their aspirations or learning and development plans. Despite available spaces, unemployment was relatively high.
The prisoner education services provider, PeoplePlus, provided a few high-quality education courses for prisoners. In English, teachers used effective strategies to enthuse and teach prisoners’ work. Prisoners made sustained progress and often achieved their intended qualifications. In subjects such as mathematics, teaching was less effective. Other subjects, such as horticulture, helped provide a balanced curriculum offer in education.
The prison reading strategy was underdeveloped. Many prisoners who needed or wanted support to improve their reading did not receive it. Although Shannon Trust supported several prisoners to improve their reading skills, reading was not promoted well enough. This was particularly evident on wings, industries and workshops.
Within many industry workshops prisoners felt a sense of purpose such as those working in the kitchens who contributed to producing food for the prison population. Prisoners working in laundry recognised the importance that their peers had clean bedding and clothing.
In kitchens, prisoners developed high quality employability skills such as arriving to work on time, teamwork and producing food to set mealtimes. They also learned how to bake different breads from raw ingredients and cook complex dishes taking account of the diverse dietary needs of the population.
Despite staff absences in roles to support prisoners with additional learning needs, staff in education supported those prisoners effectively. However, in industries and work, support for prisoners with an identified learning need was much less effective. Although all industries staff received neurodiversity training in 2024, refresher training was required.
During induction, prisoners received careers information advice and guidance about the ESW opportunities available, with an emphasis on developing prisoners’ mathematical and English skills. However, prisoners did not routinely have enough time to complete initial assessments, which caused a few delays allocating prisoners to activities.
Attendance during our visit was low. Lateness to activities was a persistent issue during our visit.
Leaders had a few enrichment activities in place for prisoners such as Italian and Spanish classes. However, beyond these, there were only a few opportunities for prisoners to participate in activities such as competitions, music or games.
Section 5: Preparation for release (Back to top)
Preparation for release is understood as a core function of the prison. Prisoners are supported to maintain and develop relationships with their family and friends. Prisoners are helped to reduce their likelihood of reoffending and their risk of harm is managed effectively. Prisoners are prepared for their release back into the community.
Children and families and contact with the outside world
Expected outcomes: The prison understands the importance of family ties to resettlement and reducing the risk of reoffending. The prison promotes and supports prisoners’ contact with their families and friends. Programmes aimed at developing parenting and relationship skills are facilitated by the prison. Prisoners not receiving visits are supported in other ways to establish or maintain family support.
Social visit arrangements were good, and the available capacity met demand.
Visitors could book appointments conveniently by telephone, email or online.
However, visitors continued to experience difficulties finding parking spaces on arrival because staff vehicles regularly occupied designated visitor bays.
The visits hall was suitably furnished and included a dedicated children’s play area. Refreshment options had improved since the previous inspection, with fruit and a couple of hot food items introduced. Despite concerns raised previously by family members, there was still no family engagement worker available to support child visitors.
Prisoners and visitors reported that seating arrangements were too close to one another, which limited privacy. Family photographs could be taken during visits, although these had to be booked in advance.


Secure social video calling (see Glossary) took place at the same time as visits, but again, the four booths did not give enough privacy.

Family services were delivered by Prison Advice and Care Trust (PACT; see Glossary), who managed a welcoming and well-run visitors’ centre. Visitors were regularly encouraged to provide feedback through surveys and family forums, and there was evidence that this had informed improvements, such as enhancements to the children’s play area.
PACT also maintained a range of structured intervention booklets designed to support family relationships. These were completed by prisoners on a one-to-one basis with a family support worker, and 59 had been completed during the previous year.
Monthly themed family days (see Glossary) were held for a range of prisoner groups and provided additional opportunities for meaningful family contact.
Staff monitored prisoners who did not receive visits, which represented around 43% of the population. Dedicated visit sessions were provided for this group, enabling them to attend the visits hall and participate in a shared social session with other prisoners. However, they were only offered twice a year.
Reducing reoffending
Expected outcomes: Prisoners are helped to change behaviours that contribute to offending. Staff help prisoners to demonstrate their progress.
Gartree held a predominantly high-risk population of prisoners, all serving life or indeterminate sentences, many of whom had been convicted of serious and often violent crimes.
More than half of all prisoners (57%) had tariffs (the minimum time in prison before release could be considered) of 10 years or longer and of those, around one-third had tariffs exceeding 15 years. About 17% of the population were over the tariff they were set when they were sentenced.
The main aim of the prison was to settle prisoners into long periods of prison life and provide opportunities for risk reduction so that they could be safely progressed, usually as directed by the parole board.
Leaders and staff involved in prisoners’ rehabilitation were well sighted on the complexities of the needs of the population, and they coordinated efforts collaboratively and flexibly in attempts to improve prisoner outcomes.
The PIPE unit, two TCs, and the ISFL unit (see Glossary) provided a structure that offered valuable opportunities for prisoners to demonstrate progress in reducing their risk (see Specialist units).
However, rehabilitative work was undermined by the absence of a sufficiently embedded community ethos beyond the specialist units, limiting opportunities to develop social capital and promote a shared sense of hope, purpose and ambition across the prison as a whole.
In our survey, only about half of prisoners said that they were less likely to reoffend as a result of their experiences in the prison.
| HMIP prisoner survey | Yes | Compared with similar prisons |
| Do you think your experiences in this prison have made you less likely to offend in the future? | 48% | No difference |
How staff were supporting prisoners and managing risk
The OMU was well led, and staff had a good understanding of their role in managing long-term prisoners through a lengthy sentence.
Work to meet the needs of specific cohorts was at an early stage but developing well. This included targeted support for young adults and those at the start of long sentences to address their individual needs.
POMs generally met prisoners promptly on arrival and sought a handover from the sending establishment to inform their understanding of each prisoner’s behaviour, risks and needs.
The OMU had worked hard to reduce the backlog of offender assessment system (OASys; see Glossary) reviews. Prisoners generally had a good awareness of their sentence plans and objectives and had been involved in developing them.
| HMIP prisoner survey | Yes | Compared with similar prisons |
| For those who have a sentence plan: Do you know what your objectives or targets are? | 81% | No difference |
| For those who have a sentence plan and knew what their objectives and targets are: Have you been involved in setting the objectives or targets? | 67% | Higher |
Prisoners approaching important stages of their sentence, such as parole board proceedings, received good support from their POMs. However, for other men – typically those in the middle of long sentences – contact was variable and did not always promote engagement and progression well enough. Despite this, we saw some examples of positive one-to-one work between POMs and prisoners.
The public protection risks associated with all new arrivals were screened promptly and thoroughly and restrictions applied and shared appropriately.
However, there were delays in reviewing phone calls for prisoners subject to offence-related monitoring, which meant that potential risks to the public were not promptly identified.
Opportunities for prisoners to progress
The programmes and psychology teams were well led under a single head of function, which promoted cohesive oversight and collaborative working across both teams. Psychology staff were well integrated into the wider prison and worked effectively with offender management and other departments. This included providing consultation to staff and contributing to some targeted one-to-one interventions alongside POMs.
The prison had introduced the Building Choices programme (see Glossary) in September 2025 and had focused delivery on the moderate-intensity strand, reflecting the profile of need. However, the accredited programme offer had been reduced as two-thirds of facilitators had been temporarily redeployed to support safer custody. There had been 22 programme completions since implementation, with a target of 25 for delivery in the next financial year.
A notable strength was the flexible approach to programme sequencing. Referrals were based on individual need rather than sentence stage, and some prisoners had commenced interventions many years before tariff expiry to allow sufficient time to consolidate learning and support progression.
Progression across the wider prison was evidenced, with 59 prisoners transferring to lower-security establishments during the previous year. Transfer waiting times were no longer excessive. At the time of the inspection there were 71 category C prisoners, with 21 waiting to be transferred (nine of whom were moving imminently), while others were either awaiting a parole hearing or engaged on a specialist unit.
There was a prison-wide approach to managing and supporting imprisonment for public protection (IPP; see Glossary) prisoners, including dedicated psychological oversight and effective case-tracking arrangements. Although there were some good outcomes for a few, including two parole board directed releases in the previous 12 months, the majority remained stuck and unable to progress through their sentence; 21 of the 44 IPP prisoners had never been released and 18 had been recalled back to custody.
Specialist units
The offender personality disorder pathway (OPD; see Glossary) units provided an impressive therapeutic environment with clear progression opportunities.
The PIPE was a 60-bed progression unit, where prisoners who had completed work to do with their offending could apply that learning in practice. The main method of intervention was the environment itself; the unit offered a strong community ethos, and staff-prisoner relationships were good with regular key working taking place. Psychologists were based on the unit, and regular structured group work was delivered.
The two small TC units also delivered intensive psychosocial interventions and demonstrated clear progression outcomes. They provided structured in-depth and intensive interventions for people with personality traits linked to their offending behaviour. Group sessions were held five times a week complemented by regular check-ins. The TC-plus unit provided similar interventions but for prisoners with learning difficulties, specifically low IQ level. These prisoners were supported at a pace appropriate to their learning needs.
Returning to the community
Expected outcomes: Prisoners’ specific reintegration needs are met through good multi-agency working to maximise the likelihood of successful resettlement on release.
All the population were eligible for multi-agency public protection arrangements (MAPPA; see Glossary), and the majority were assessed as posing a high/very high risk of serious harm to others. Many prisoners were subject to public protection contact restrictions or had histories of perpetrating domestic abuse.
The weekly and monthly interdepartmental risk management meetings were effective in assessing and managing risk and routinely considered prisoners at appropriate intervals.
Contributions to MAPPA meetings were good, reflecting POMs’ strong understanding of prisoners and factors driving their behaviour.
HMP Gartree did not have any resettlement services as there was rarely any need. Prisoners released directly into the community all required direction by the parole board and Secretary of State approval.
Practical and risk release planning arrangements relied on the OMU, various prison departments and community probation teams working collaboratively, which they did very well. Pre-release planning was thorough and mindful of risk.
The two prisoners released in the previous 12 months went to probation-approved premises as a requirement of their licence conditions. The release of another prisoner, due to happen shortly after our inspection, was being carefully planned.
Section 6: About HMP Gartree (Back to top)
Please note, much of the following information was supplied by the establishment at the time of the inspection.
Category of the prison
HMP Gartree is a category B training prison for adult men.
Brief history
HMP Gartree, near Market Harborough, first opened in 1965 as a category C male training prison and became a category B male prison within the high security system in 1992. In 1997, its role changed to a life-sentenced prisoner centre. In 2017, the prison became part of the long-term high security estate (LTHSE), with an emphasis on housing prisoners serving indeterminate and long-term sentences.
Population
631 prisoners were held at the time of the inspection. There was operational capacity (see Glossary) for 697.
- All prisoners were serving indeterminate sentences.
- 175 new prisoners were received in the last 12 months.
- 148 prisoners were within the first five years of a long sentence.
- 41 were young adults (under 25 years of age).
- 75 were over 60 years of age.
- 85 were foreign national prisoners, comprising 37 different nationalities.
- 44 were IPP prisoners.
- 40% of the population were from black and ethnic minority backgrounds.
- 110 prisoners were receiving substance support from Inclusion (NHS psychological substance misuse service).
Short description of residential units
A, B, C and D wings: non-specialist units, each containing 96–100 prisoners. D wing also includes a first night and induction function
G wing: houses 120 prisoners, includes a ‘violence reduction landing’ of up to 30 prisoners
H wing: 60 prisoners on the over-50s unit and 60 on the psychologically informed planned environment (PIPE) unit
I wing (the Acorn Unit): incentivised substance-free living (ISFL) unit for 19 prisoners
Therapeutic community (TC): 25-bed therapeutic unit
Therapeutic community plus: 12-bed unit operating the TC model for prisoners
with learning difficulties and/or disabilities
Segregation unit: up to 12 prisoners held in segregated conditions
Prison status (public/private)
Public – HMPPS
Key providers
Physical health provider: Practice Plus Group
Mental health provider: Practice Plus Group
Substance misuse treatment provider: Practice Plus Group
Substance misuse psychosocial provider: Practice Plus Group, subcontracted to Midlands Partnership University NHS Foundation Trust (MPFT) Inclusion Service
Dental health provider: Practice Plus Group, subcontracted to Time for Teeth
Prison education framework provider: PeoplePlus Group
Escort contractor: GeoAmey
Prison group director
Gavin O’Malley
Name of governor/director and date in post
Rachel Jones Acting Governor from November 2023, and Governor from June 2025
Changes of governor/director since the last inspection
Babafemi Dada from 2019 to 2023
Independent Monitoring Board Chair
Steve Martin
Date of last inspection
16–26 January 2023
Progress on concerns from the last inspection (Back to top)
.At our last inspection in 2023 we raised 11 concerns, six of which were about areas of priority concern.
At this inspection we found the following progress:
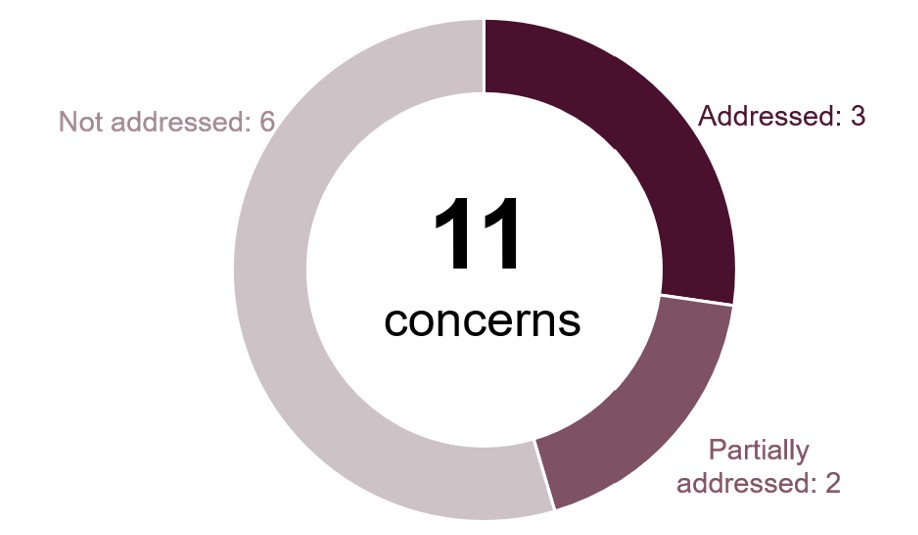
The following is a list of all the concerns raised, organised under the four tests of a healthy prison.
Safety
Priority concern
Too many illicit items, including drugs, were entering the prison. Although security measures had been improved, further action was needed to reduce supply.
Not addressed
Respect
Priority concerns
The prison environment was poor, and the fabric of the buildings was in a state of disrepair.
Not addressed
Many communal areas were dirty. Standards were not high enough and monitoring of day-to-day cleaning was not robust.
Not addressed
Key concern
The care for patients with long term conditions was inconsistent.
Addressed
Purposeful activity
Priority concerns
There were far too many interruptions to education, skills and work activities. We evidenced poor attendance and delays in the completion and achievement of qualifications in education. Similar issues also undermined the efficiency and working ethos of workshops.
Not addressed
There was insufficient support for prisoners with learning difficulties and disabilities and those with low reading ability.
Addressed
The curriculum did not fully meet the needs of the prison population.
Not addressed
Key concerns
The quality of learning and skills provision had not been improved promptly or effectively. Leaders’ improvement plans did not effectively identify and drive improvement and none of the recommendations from the previous inspection had been fully met.
Not addressed
The collection and analysis of data were underdeveloped. Data were not used well to evaluate the performance of education, skills and work.
Partially addressed
Preparation for release
Key concerns
Too many OASys (offender assessment system) assessments were overdue. Nearly 200 prisoners needed an assessment completed to inform their management and progression.
Partially addressed
Prisoners who were recategorised to category C were not being transferred to lower category prisons, delaying and restricting their opportunity to progress through their sentence. There were over 100 category C prisoners at Gartree.
Addressed
Care Quality Commission Action Plan (Back to top)
Care Quality Commission (CQC) is the independent regulator of health and adult social care in England. It monitors, inspects and regulates services to make sure they meet fundamental standards of quality and safety. For information on CQC’s standards of care and the action it takes to improve services, please visit: http://www.cqc.org.uk
The inspection of health services at HMP Gartree was jointly undertaken by the CQC and HMI Prisons under a memorandum of understanding agreement between the agencies (see Working with partners) for action plans following this inspection. The Care Quality Commission issued a request for an action plan following this inspection.
Provider: Practice Plus Group
Location: HMP Gartree
Location ID: 1-18390351018
Regulated activities: Diagnostic and screening procedures, Personal care and Treatment of disease, disorder or injury.
Action we have told the provider to take
This notice shows the regulations that were not being met. The provider must send CQC a report that says what action it is going to take to meet these regulations.
Regulation 17 Good governance
17 (1) Systems or processes must be established and operated effectively to ensure compliance with the requirements in this Part.
17 (2) Without limiting paragraph (1), such systems or processes must enable the registered person, in particular, to:
- assess, monitor and improve the quality and safety of the services provided in the carrying on of the regulated activity (including the quality of the experience of service users in receiving those services);
- assess, monitor and mitigate the risks relating to the health, safety and welfare of service users and others who may be at risk which arise from the carrying on of the regulated activity;
How the regulation was not being met:
Governance of pharmacy services was weak:
- The staffing model includes 0.3 WTE of a pharmacist, but there was no regular on site visits or oversight from a pharmacist.
- Patients did not have access to pharmacy led clinics.
- Medicines management meetings had not taken place for over three months.
- Some written procedures were out of date and had not been updated.
- Medicines cabinets in the pharmacy did not meet the required standards and did not lock.
Patients had very limited access to psychological therapies:
- Access to psychological therapies was limited to one practitioner with a small caseload which was insufficient to meet the needs of the prison population and was contrary to the local mental health operating procedure.
- The waiting list for ‘psychological therapies groups’ included 13 patients who had all waited over 36 weeks with the longest waiting over 2 years.
- The waiting list for ‘psychological therapies assessment’ included 22 patients waiting up to 1 year 31 weeks.
- The waiting list for ‘psychological therapies waiting for treatment’ included 4 patients who had waited 49, 45, 44 and 40 weeks.
More about this report (Back to top)
This report outlines the priority and key concerns from the inspection and our judgements against the four healthy prison tests. Each of the following four sections contains a detailed account of our findings against our Expectations for men’s prisons.
Find out more about our Expectations and how we inspect
Find out more about priority and key concerns
Find out about notable positive practice
Findings from the survey of prisoners and a detailed description of the survey methodology are published alongside this report. Please note that we only refer to comparisons with other comparable establishments or previous inspections when these are statistically significant. The significance level is set at 0.01, which means that there is only a 1% chance that the difference in results is due to chance.
The tables in this report which provide data from HMI Prisons prisoner surveys also include comparisons with similar prisons.
| Description | What it means |
| Lower | the prison’s percentage is statistically significantly lower than the comparator: prisons with the same function type, or at the last inspection |
| Higher | the prison’s percentage is statistically significantly higher than the comparator: prisons with the same function type, or at the last inspection |
| No difference | the prison’s percentage is not statistically significantly different to the comparator: prisons with the same function type, or at the last inspection |
Inspection team
This inspection was carried out by:
Martin Lomas, Deputy Chief inspector
Sara Pennington, Team leader
Harriet Leaver, Inspector
Jade Richards, Inspector
Rick Wright, Inspector
Nadia Syed, Inspector
Dawn Mauldon, Inspector
Sam Moses, Researcher
Joe Simmonds, Researcher
Tareek Deacon, Researcher
Alicia Grassom, Researcher
Angela Star, Lead health and social care inspector
Sarah Goodwin, Health and social care inspector
Dayni Johnson, Care Quality Commission inspector
Ian Frear, Lead Ofsted inspector
Hilary Speight, Ofsted inspector
Mary Devane, Ofsted inspector
Corine Baker, Ofsted inspector
Find out more about the terms and abbreviations used in this report in our glossary.
Easy read summary and press notice (Back to top)
Survey materials and Ofsted full report (Back to top)
The following files may not be suitable for users of assistive technology.
Request an accessible format
If you use assistive technology (such as a screen reader) and need a version of any of these documents in a more accessible format, please email media@hmiprisons.gov.uk. Please tell us what format you need. It will help us if you say what assistive technology you use.